Operations
Reconciling a Dental Membership Plan
Quick Answer
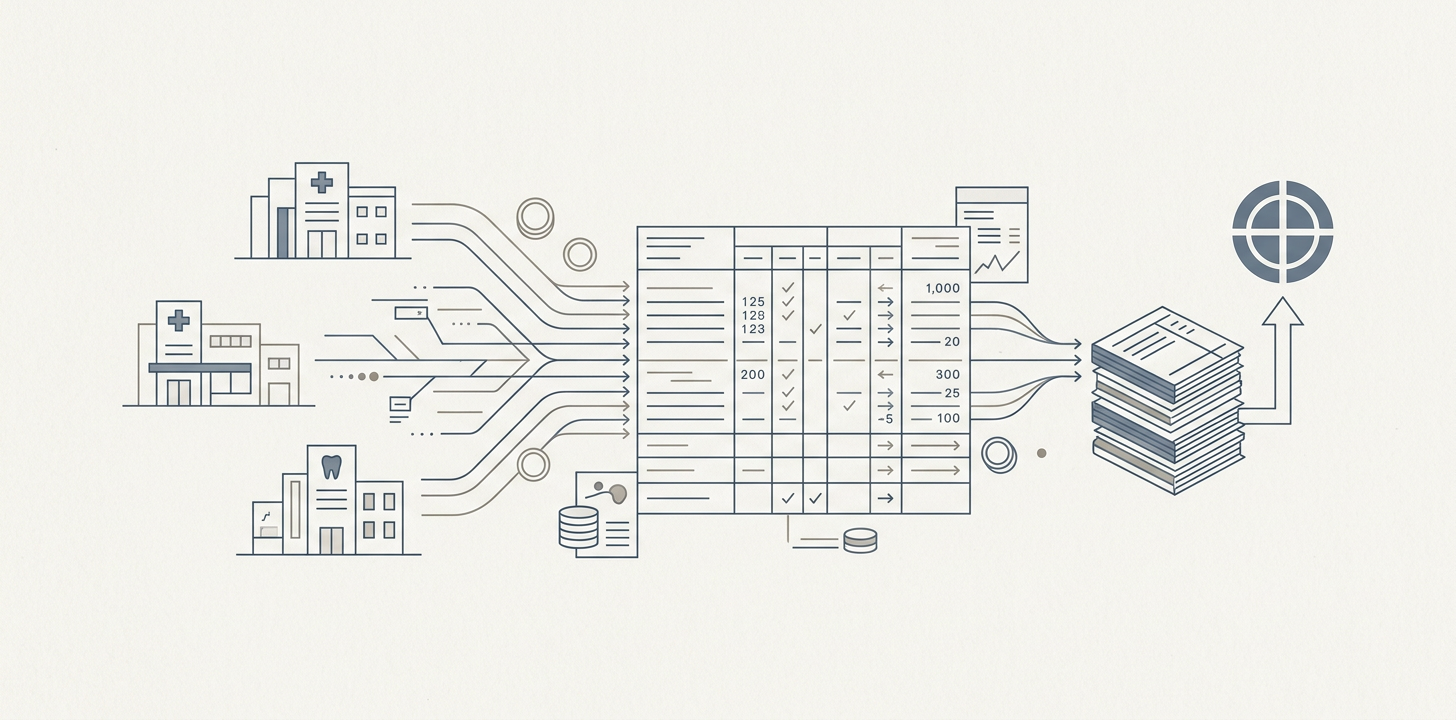
A group dental membership plan only holds up when four monthly numbers tie out per location, namely active paid members against PMS flags, membership fees posted against deposits, discount write-offs by adjustment type, and included-service production given to members. A per-location profit and loss then shows net plan contribution, which differs from the recurring revenue a vendor dashboard reports and shows where the plan should expand or pause.
Your membership platform can say 1,400 active members and still be wrong in a way that matters to finance. At group scale, the real question is not if the dashboard shows recurring revenue. It is if the vendor, the PMS ledger, and the bank agree on who is active, what was collected, what was written off, and what the plan actually cost each location.
The short answer is that an in house dental membership plan is only as good as the ledger behind it. If you run the plan across multiple offices, we check four numbers every month per location. Compare active paid members in the membership platform to active members flagged in the PMS, membership fees posted in the PMS to deposits in the bank or GL, discount write-offs by adjustment type, and included-service production given away to members. If those do not tie out, the MRR in the dashboard is not the same thing as plan economics.
That sounds basic, but it is the part most plan software does not solve for a multi-location group. The vendor handles enrollment, billing, and the member-facing side. The PMS handles production and adjustments. Finance handles cash. The gap appears when those systems have to answer one question together.
What an In-House Dental Membership Plan Actually Is
An in-house dental membership plan is a direct-to-patient subscription offered by a practice or group. The patient pays a recurring fee, preventive care is usually included, and other services may be discounted. It is not insurance. In many setups, the plan is presented as a membership or savings plan rather than a risk-transfer product, which is why many practices follow ADA guidance on in-office dental plans and vendor compliance guidance when they describe it.
For a single office, that definition is usually enough. For a 5-50 location group, we think the plan becomes a financial system, not just a marketing offer. Once you add multiple PMS instances, regional fee differences, and different front-office workflows, the question changes from “Can we sell this?” to “Can we prove it is working?”
Three Systems and Three Versions of the Truth
We usually see three different records of the same plan.
- The membership platform knows who enrolled, who paid, who lapsed, and what the vendor thinks recurring revenue is.
- The PMS ledger knows the patient account, posted adjustments, production, and if the member is still flagged active inside the practice system.
- The bank or general ledger knows what actually hit cash and when the deposits cleared.
Each system is useful, but none of them is complete on its own. The vendor may know a card failed yesterday, while the PMS still shows the patient as eligible. The PMS may show a discount adjustment, while finance classifies it as a generic courtesy write-off. The bank may show a deposit, while the platform has not yet recognized the fee because of timing or a processor hold.
The job of a finance lead is not to force all three systems to say the same thing in every field. It is to decide which numbers should reconcile every month and which ones are allowed to differ because they measure different things.
The Four Monthly Reconciliations That Matter
We run these four checks every month, per location.
1. Active Paid Members
What it is. Members who are current in the membership platform and should be receiving plan benefits.
Where it breaks. Failed cards, canceled plans not marked inactive in the PMS, or manual overrides that keep a member flagged active after payment stopped.
How to detect it. Pull a monthly list of active members from the vendor and compare it to active membership flags in the PMS by location. Then isolate accounts with no successful payment in the last billing cycle but still receiving member pricing or included preventive care.
The point is not only counting members. It is finding people who look active in one system and inactive in another, because those are the patients most likely to receive benefits without payment.
2. Membership Fees Posted Versus Deposits
What it is. The membership fees the PMS or accounting system shows as posted, versus what actually cleared the bank.
Where it breaks. Processor timing, refunds, chargebacks, split deposits across locations, or revenue recorded in a central entity while collections flow through an office-level account.
How to detect it. Compare the month’s membership fee postings in the PMS to the bank deposit total and the processor settlement report. The totals should match after timing differences are explained. If they do not, you need a specific reason, not a generic “pending reconciliation” note.
Groups often discover that the dashboard’s recurring revenue is directionally useful but not the same as collected cash. That distinction matters when the plan is being used to support staffing or offset hygiene capacity.
3. Discount Write-Offs by Adjustment Type
What it is. The value of discounts given to members when a procedure is billed below standard fee schedule.
Where it breaks. Membership discounts get mixed with PPO contractual adjustments, courtesy adjustments, bad-debt write-offs, or provider discounts. Once that happens, nobody can tell if the plan is generating strategic write-offs or just hiding general discounting.
How to detect it. Create a distinct adjustment type in the PMS for membership-plan discounts and keep it separate from insurance write-offs and courtesy write-offs. In Open Dental, for example, the Discount Plans feature assigns an adjustment type to each plan, and a Discount Plans report lists them. Then review monthly adjustment totals by location. If a location has membership activity but no membership-specific adjustment code, the discount is probably being buried somewhere else.
This matters because a membership plan has a known price and a known discount structure. If the discount is not isolated, you cannot measure its cost or compare locations fairly.
4. Included-Service Production Given to Members
What it is. The preventive services and any other included care the member used at no additional charge under the plan.
Where it breaks. A member lapses in the vendor system but still receives covered hygiene, or the PMS still treats the patient as active because no one updated eligibility status at checkout.
How to detect it. Compare the list of lapsed or failed-payment accounts in the vendor platform to preventive services posted in the PMS after lapse date. The question is not only if the office provided care. It is if the office provided care to a patient who should have lost benefit eligibility.
In a single practice, this kind of leakage may be small. Across many offices, it becomes a pattern. And once the pattern exists, it is hard to untangle after the fact because the revenue impact is spread across dozens or hundreds of appointments.
How to Measure Plan Profitability per Location
To see if the plan is worth it, you need a per-location P&L, not just a company-wide member count. We keep the model simple enough that finance can run it every month.
A practical template looks like this:
- Membership fee revenue collected
- Minus processor and vendor fees
- Minus membership discount write-offs
- Minus the value of included services delivered to members
- Minus the chair time or production capacity you would otherwise have used for paying patients
- = Net plan contribution by location
That last line is the one owners care about. It answers a different question than MRR. MRR tells you how much recurring fee revenue the plan generated. Net contribution tells you if the office made money after giving away benefits and discounts.
If you want a better comparison, measure the same cohort of patients before they joined the plan. Look at their production and visit pattern over the prior 12 months. Then compare it to the 12 months after enrollment. Use the same office, or at least the same region, so differences in payer mix or fee schedule do not distort the result. The point is to estimate if the plan changed behavior enough to justify the included care and discounts.
Do not use a broad company average if one location has mostly preventive-heavy patients and another has more restorative work. That will hide the site-level economics that matter when you decide where to expand the plan and where to pause it.
How to Read Vendor Claims Without Getting Fooled by Them
Vendors often publish impressive uplift numbers. A claim like “172% production lift” may be directionally useful, but it is usually a self-reported comparison. It can be true for the cohort they chose and still be misleading for your group.
Test the claim on your own data the way we would, with a simple before-and-after cohort:
- Pick patients who enrolled in the plan during a fixed month or quarter.
- Measure their production in the 12 months before enrollment.
- Measure their production in the 12 months after enrollment.
- Separate by location, because office mix matters.
- Exclude patients who moved, changed insurers, or had unusual one-time treatment if you want a cleaner read.
Then ask one hard question. Did the plan increase production, or did it mostly attract patients who were already likely to spend? Self-selection is a real issue. People who enroll in membership plans are often more price-sensitive and more likely to accept treatment when they see a known discount. That can help production. It can also make the uplift look better than the plan itself deserves.
What the Platforms Do Well and Where They Stop
Most dental membership plan software does a decent job at the member-facing workflow. It can enroll patients, run billing, send reminders, and present a clean compliance story. Some products also advertise PMS integration, and newer links can reduce manual work in Open Dental, Dentrix, Eaglesoft, or Denticon environments.
That is useful, but in our view it is not the same as a finance-grade reporting layer. A platform that can sync enrollment status may still leave you with separate views of discounts, write-offs, and deposits. If you run one office, that gap may be manageable. If you run 20 offices on different versions of the PMS, it becomes a monthly close problem.
This is why the right question is not “Which plan software has the best dashboard?” It is “Which setup gives us one clean monthly truth at location level?” Sometimes the answer is better integration. Sometimes it is a reporting layer on top of the vendor and PMS data.
When a Group Should Build the Reporting Layer
At some point, the simplest adequate answer is not another dashboard from the vendor. It is a read layer that combines the PMS, the membership platform, and the bank or general ledger into one reporting model.
That usually starts making sense when most of these are true:
- You have 10 or more locations.
- You run multiple PMS instances or versions.
- Your membership plan changes by region or office.
- Finance is closing the books with spreadsheets and manual exports.
- Leadership wants location-level profit, not just system-level enrollment metrics.
When those conditions show up, the cost of not reconciling usually grows faster than the cost of building the reporting layer. The build is not a replacement for the membership platform. It is the control surface that tells you if the platform is doing its job.
That is the kind of layer we have built for multi-location operators, including reporting and business operations across a large dental group. Apex Dental Partners is a good example of the sort of cross-practice reporting problem groups run into once the number of locations gets large enough that spreadsheets stop being enough. For more on how we work in this space, see our healthcare software development page, or read how the same problem shows up in scoring an unscheduled treatment report and dental lab case tracking for multi-location groups.
A Practical Monthly Close for Your Finance Lead
If you want to start this week, we would not ask for a full system overhaul. Ask for one monthly report per location with four rows:
- Active paid members
- Membership fees collected and posted
- Membership discount write-offs
- Included preventive production delivered
Then add two checks. First, identify failed-payment members who still showed up as active in the PMS. Second, compare plan-enrolled patients’ production before and after enrollment using a fixed cohort window.
If the numbers tie out, you have a real operating model. If they do not, you have a data and process problem that will keep affecting revenue recognition, chair utilization, and location-level profit. That is the whole point of reconciling a dental membership plan every month. To see how we work on this kind of problem, start with Better Software.
Frequently Asked Questions
Are In-House Dental Plans Worth It?
For a multi-location group, we find the plan is worth it only if the net contribution stays positive after discounts, included care, and operating overhead. The right test is a per-location P&L, not total member count. If it fills hygiene chairs without giving away too much production, it can work.
What Is In-House Dental Insurance?
It is usually a loose way of describing a membership plan, and we are clear that it is not insurance. Insurance transfers risk under regulated rules, while a membership plan is a direct arrangement between the practice and the patient for included preventive services and discounts. Use language that fits your state rules.
How Do Membership Discounts Post in the PMS?
We post them as a distinct membership-plan adjustment type, separate from PPO contractual write-offs, courtesy adjustments, and bad-debt write-offs. If they are mixed together, you lose the ability to measure plan cost or compare locations consistently. Open Dental, for example, lets each discount plan carry its own adjustment type.
What Happens When a Member Card Fails?
In a clean process, the member is marked inactive in the vendor platform, the PMS eligibility flag is updated, and front-office staff are alerted before the next included visit. If the PMS still shows the patient as active, the office may keep giving benefits after payment has stopped, which is the leakage we want the monthly reconciliation to catch.
What Is an In-House Dental Membership Plan?
It is a direct-to-patient subscription offered by a practice or group. The patient pays a recurring fee, preventive care is usually included, and other services may be discounted. We treat it as a financial system in a multi-location group, not just a marketing offer.
About the author

Better Software Team
Product and engineering team
Better Software Team is the product and engineering team at Better Software. We build custom software for established businesses in healthcare, energy and finance.